Blood-Sparing Heart Surgery With Cardio-pulmonary Bypass: Limiting the Use of Blood Products for Repair of Congenital Heart Disease
Blood-Sparing Heart Surgery With Cardio-pulmonary Bypass: Limiting the Use of Blood Products for Repair of Congenital Heart Disease https://pediatricsnationwide.org/wp-content/uploads/2026/10/081015ds0175HR-crop.jpg 432 351 Katie Brind'Amour, PhD, MS, CHES https://pediatricsnationwide.org/wp-content/uploads/2021/03/Katie-B-portrait.gif
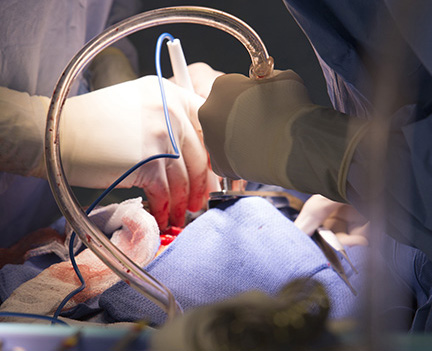
More than two decades of work suggest that not only can complicated cardiac surgeries be done without blood transfusions but the outcomes are likely just as good as the traditional approach.
For the multidisciplinary team of clinicians at Nationwide Children’s, blood transfusion and cardio-pulmonary bypass (CPB) operations are not inseparable concepts. What started out as an endeavor to better serve patients with religious objections to blood transfusions has morphed into a decades-long study of safe protocols to minimize exposure to homologous blood products, a process called blood conservation, for all patients.

Sergio A. Carrillo, MD
“Blood transfusions are expensive, and they carry risks of infection, immunologic reactions, inflammation and fluid overload,” says Sergio A. Carrillo, MD, pediatric cardiothoracic surgeon in The Heart Center, surgical director of the Adult Congenital Heart Disease (ACHD) program at Nationwide Children’s and lead author of a recently published expert opinion outlining the team’s blood-sparing protocol and approach. “If you are a parent of a child undergoing cardiac surgery, and the outcomes are equivalent with or without the use of blood products, plus you could avoid the risk of inflammation and infection from transfusions, that’s something worth considering.”
For these reasons, as well as a general scientific inquiry into whether blood transfusion and CPB are linked because of necessity rather than historical practice, Dr. Carrillo and his team have begun to approach every case as a blood-sparing operation.
“We’re not talking about transfusion-free surgery at any cost,” says Dr. Carrillo. “We evaluate each patient individually and attempt a blood-sparing procedure whenever possible without endangering the patient or putting them at undue risk.”
The multidisciplinary team exercises a holistic view about blood-sparing practices. This takes into consideration not just what happens during the operation, but also the pre-operative preparation and post-operative intensive care. Their latest data show that from 2020 and 2025, Nationwide Children’s performed 1,450 CPB procedures on 1,322 patients for congenital heart disease using the team’s blood-sparing protocol. Of those, 499 (34%) were completed without exposure to transfused blood products throughout the hospitalization.
Bloodless surgery was associated with a 53% shorter hospital stay (4.4 days vs 9.4 days for the transfusion group) and 62% shorter intensive care unit stay (1.1 days vs 3.0 days for the transfusion group). Older children were more likely to complete bloodless stays than neonates.
A major challenge in congenital heart surgery is that the volume needed to prime a bypass circuit can approach the amount of blood circulating in a small infant’s body, historically making transfusion a routine component of many CPB-supported procedures.
As they refine their protocol, increasingly small patients and complex cases are being completed without transfusion. Dr. Carrillo cites four recent bloodless congenital heart surgeries performed in infants younger than 1 year of age, including one performed in a 2-day-old, 3.7-kilogram newborn requiring complex cardiac repair with CPB.
“As a surgeon, I might be leading the charge, but I need a dedicated team behind me to support that ideology and make it happen,” Dr. Carrillo explains.
He believes that a shared commitment to blood-sparing practices is one of the most important lessons for other institutions interested in adopting similar practices.
The team’s protocol begins long before a patient enters the operating room. For newborns, strategies such as delayed umbilical cord clamping increase circulating blood volume before surgery. During hospitalization, care teams minimize unnecessary blood sampling, optimize nutrition and hydration, maintain normothermia and avoid excess fluid administration.
In the operating room, customized low-prime CPB circuits and techniques such as acute normovolemic hemodilution and autologous blood priming help reduce hemodilution and preserve the patient’s own blood volume. Postoperatively, intensive care teams continue blood-conservation efforts.
Importantly, patient safeguards remain central throughout the process. Although hematocrit targets help guide care, transfusion decisions are based on each patient’s overall physiologic status, including measures of oxygen delivery and tissue perfusion. Blood products remain available whenever needed.
“We maintain the highest standard of care and attention to safety,” says Dr. Carrillo. “We’re simply trying our best to limit exposure. If we can’t achieve a completely blood-sparing procedure, we can often still significantly reduce utilization of blood products.”
To date, mortality among patients undergoing bloodless operations has remained very low; among the 499 bloodless CPB cases performed during the study period, unadjusted in-hospital mortality was 0.22%.
For Dr. Carrillo, however, the significance of the work extends beyond any single outcome measure.
“It’s really about challenging the dogma: Why is it that we think blood transfusions are even required?” he asks. “We’re not saying transfusions are wrong. We’re asking whether they are always necessary.”
That question has implications for broader quality improvement efforts to reduce the total volume of blood transfused and minimize waste, particularly for infants, in partnership with the blood bank.
“We believe strongly in following the evidence to create true best practices,” says Dr. Carrillo. “If we can provide the optimal care patients deserve, while reducing exposure to blood products and the risks that come with them, then we owe it to patients to keep exploring those possibilities.”
Reference:
- Carrillo SA, Chenault K, Naguib AN, Voss J, Kelly M, Shutes B, Fitch JA, Blais B, Yerebakan C, Galantowicz M. Multidisciplinary blood conservation practices for transfusion-free congenital heart surgery. J Thorac Cardiovasc Surg. 2026 Jul;172(1):209-215.e2.
- Bagrodia N, Naguib A, McConnell P, Galantowicz M, Yerebakan C, Shinoka T, Carrillo S. Evaluating blood conservation practices during congenital heart surgery: a 6-year appraisal. Abstract. Western Thoracic Surgical Association Annual Meeting, 2026. Accessed September 25, 2026. https://meetings.westernthoracic.org/Program/2026/RF26.cgi
Image credit: Nationwide Children’s
About the author

Katherine (Katie) Brind’Amour is a freelance medical and health science writer based in Pennsylvania. She has written about nearly every therapeutic area for patients, doctors and the general public. Dr. Brind’Amour specializes in health literacy and patient education. She completed her BS and MS degrees in Biology at Arizona State University and her PhD in Health Services Management and Policy at The Ohio State University. She is a Certified Health Education Specialist and is interested in health promotion via health programs and the communication of medical information.
- Katie Brind'Amour, PhD, MS, CHEShttps://pediatricsnationwide.org/author/katie-brindamour-phd-ms-ches/

- Katie Brind'Amour, PhD, MS, CHEShttps://pediatricsnationwide.org/author/katie-brindamour-phd-ms-ches/
- Katie Brind'Amour, PhD, MS, CHEShttps://pediatricsnationwide.org/author/katie-brindamour-phd-ms-ches/
- Katie Brind'Amour, PhD, MS, CHEShttps://pediatricsnationwide.org/author/katie-brindamour-phd-ms-ches/